
Sleepless nights.
Gas that makes your baby wither in pain.
Constant crying (from both you and the baby) that breaks your heart.
Watching your baby in pain, not knowing how you can help.
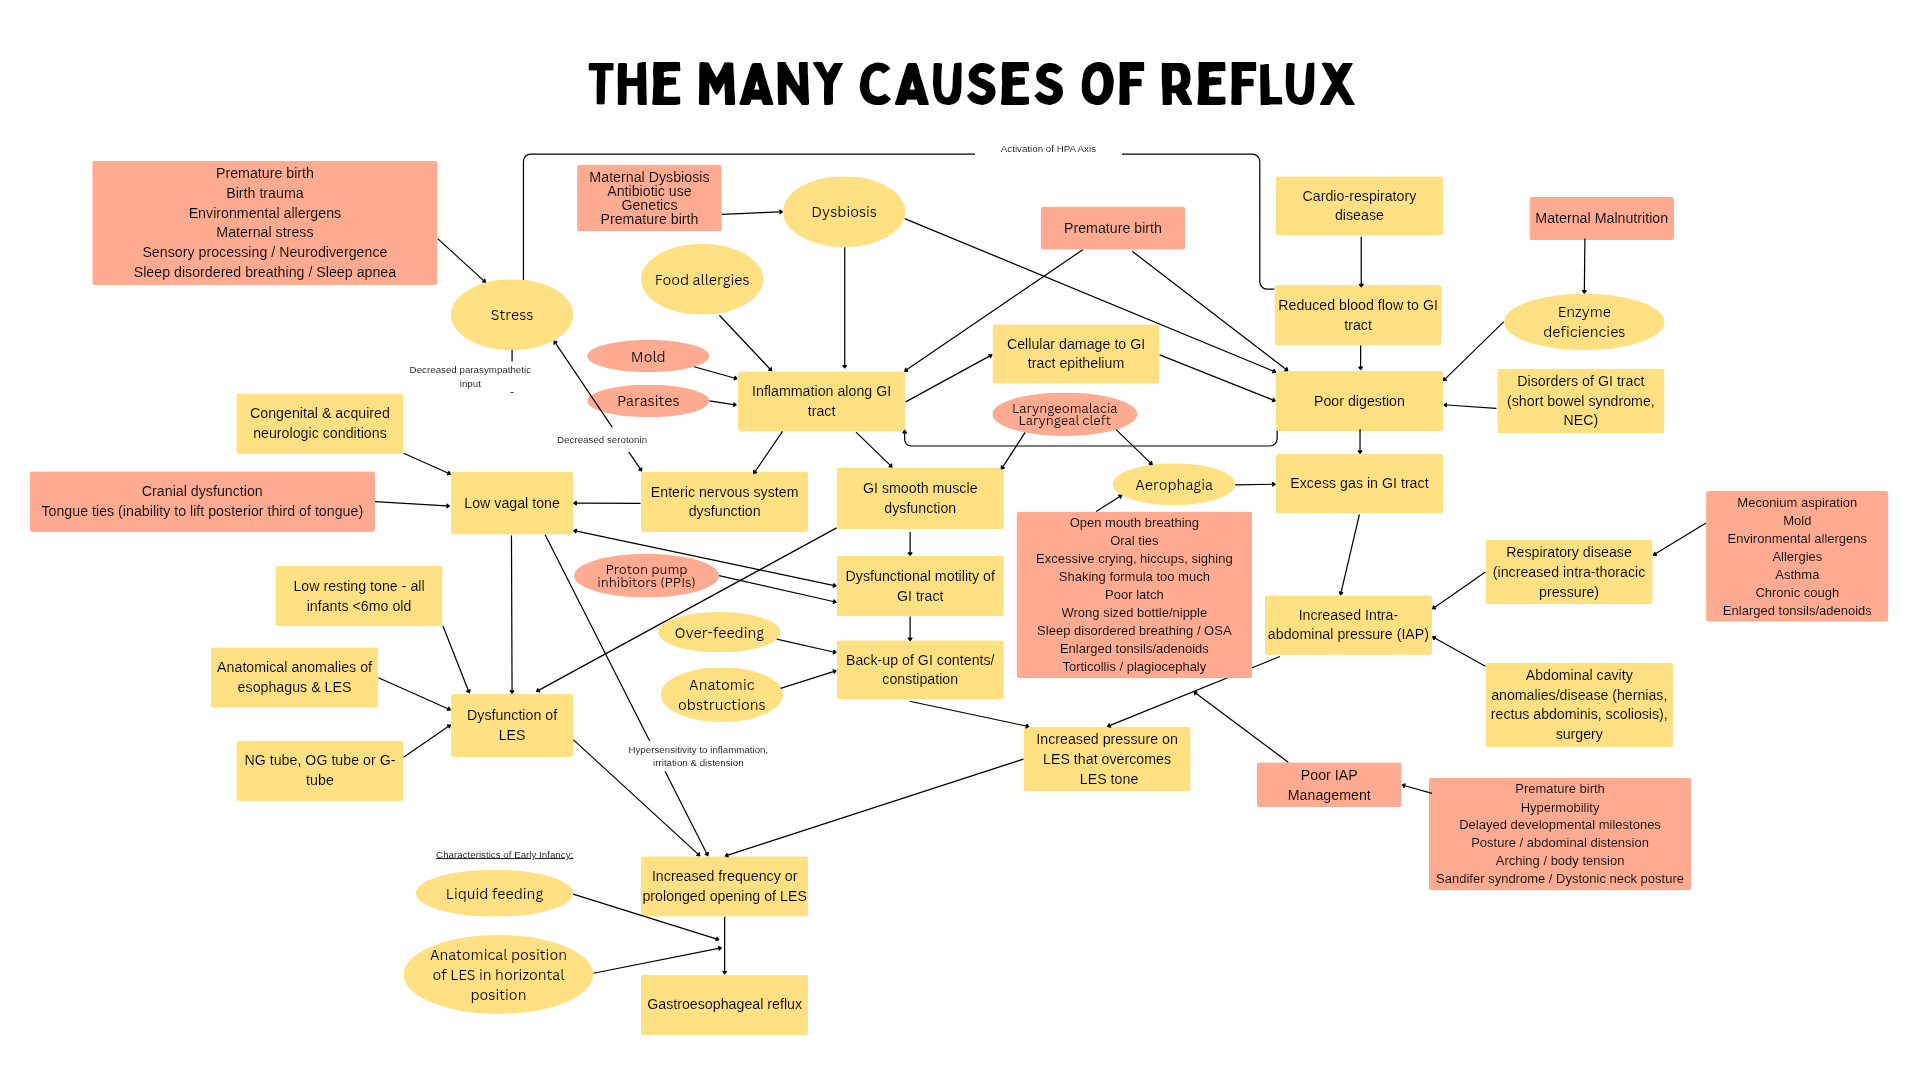
Having an infant with reflux can be hard and not knowing what your next steps to help them can be even harder. Let's break down the many causes of reflux. Hopefully you can get your little one to a provider who can help both of you take the next steps forward to helping your little one.
What is infant reflux?
Beyond discomfort, irritability, excessive crying, back arching and breast/bottle refusal, infant reflux is when the lower esophageal sphincter (think of this as a little valve that goes from the esophagus to the stomach) relaxes and opens after swallowing to allow food to move from the esophagus to the stomach. It should remain closed when not actively digesting food. When a baby has reflux, the sphincter stays open and allows normal stomach acid to flow upward.
A lot of babies are given proton pump inhibitors (lansoprazole) and histamine-2 receptor antagonists (ranitidine) to help with the reflux. Unfortunately, research has shown that those medications aren't really effective at reducing GERD symptoms. The reason these medications aren't always effective is because it assumes that reflux is caused by excess acid. In many cases, the acid is actually secondary to the root cause(s) of reflux or it isn't acid at all, but actually excess air that is coming upwards causing the discomfort. That's why it is important to look at ALL of the causes of reflux as there may be more than one!
What is normal infant reflux?
There are two main forms of reflux, those labeled “happy spitters” and those whose parents are tired of cleaning spit up off of walls, car doors and spending countless hours trying to calm their baby.
Happy spitters are babies that have a little bit of spit up. This usually isn't a lot of spit up and the child seems unphased. Reflux babies typically struggle in their day-to-day activities, find sleep nearly impossible, they may be losing weight or eating all of the time to counteract what they lose in their spit-up. This blog is about the latter.
What causes of infant reflux?
First, let's look at the NORMAL (not just common, but truly normal) causes of reflux.
Weak LES and reflux
Babies are born with a weak lower esophageal sphincter (LES). Basically the sphincter needs time to strengthen so it can fully close. When a baby is born prematurely, this is even more common. Infants quite literally have half of the pressure as adults and preemies have ⅙ the pressure to help keep the LES closed. {{Nerd facts: A full-term infant has a resting tone of 18mmHg and babies that are born at 35-36 weeks have a pressure of 12mmHg and babies born at 27-28 weeks have a pressure of 3.8mmHg. For comparison, adult pressure is usually closer to 25mmHg.}} This isn't meant to scare you, but to let you know that most of these infants grow out of reflux as they get older.
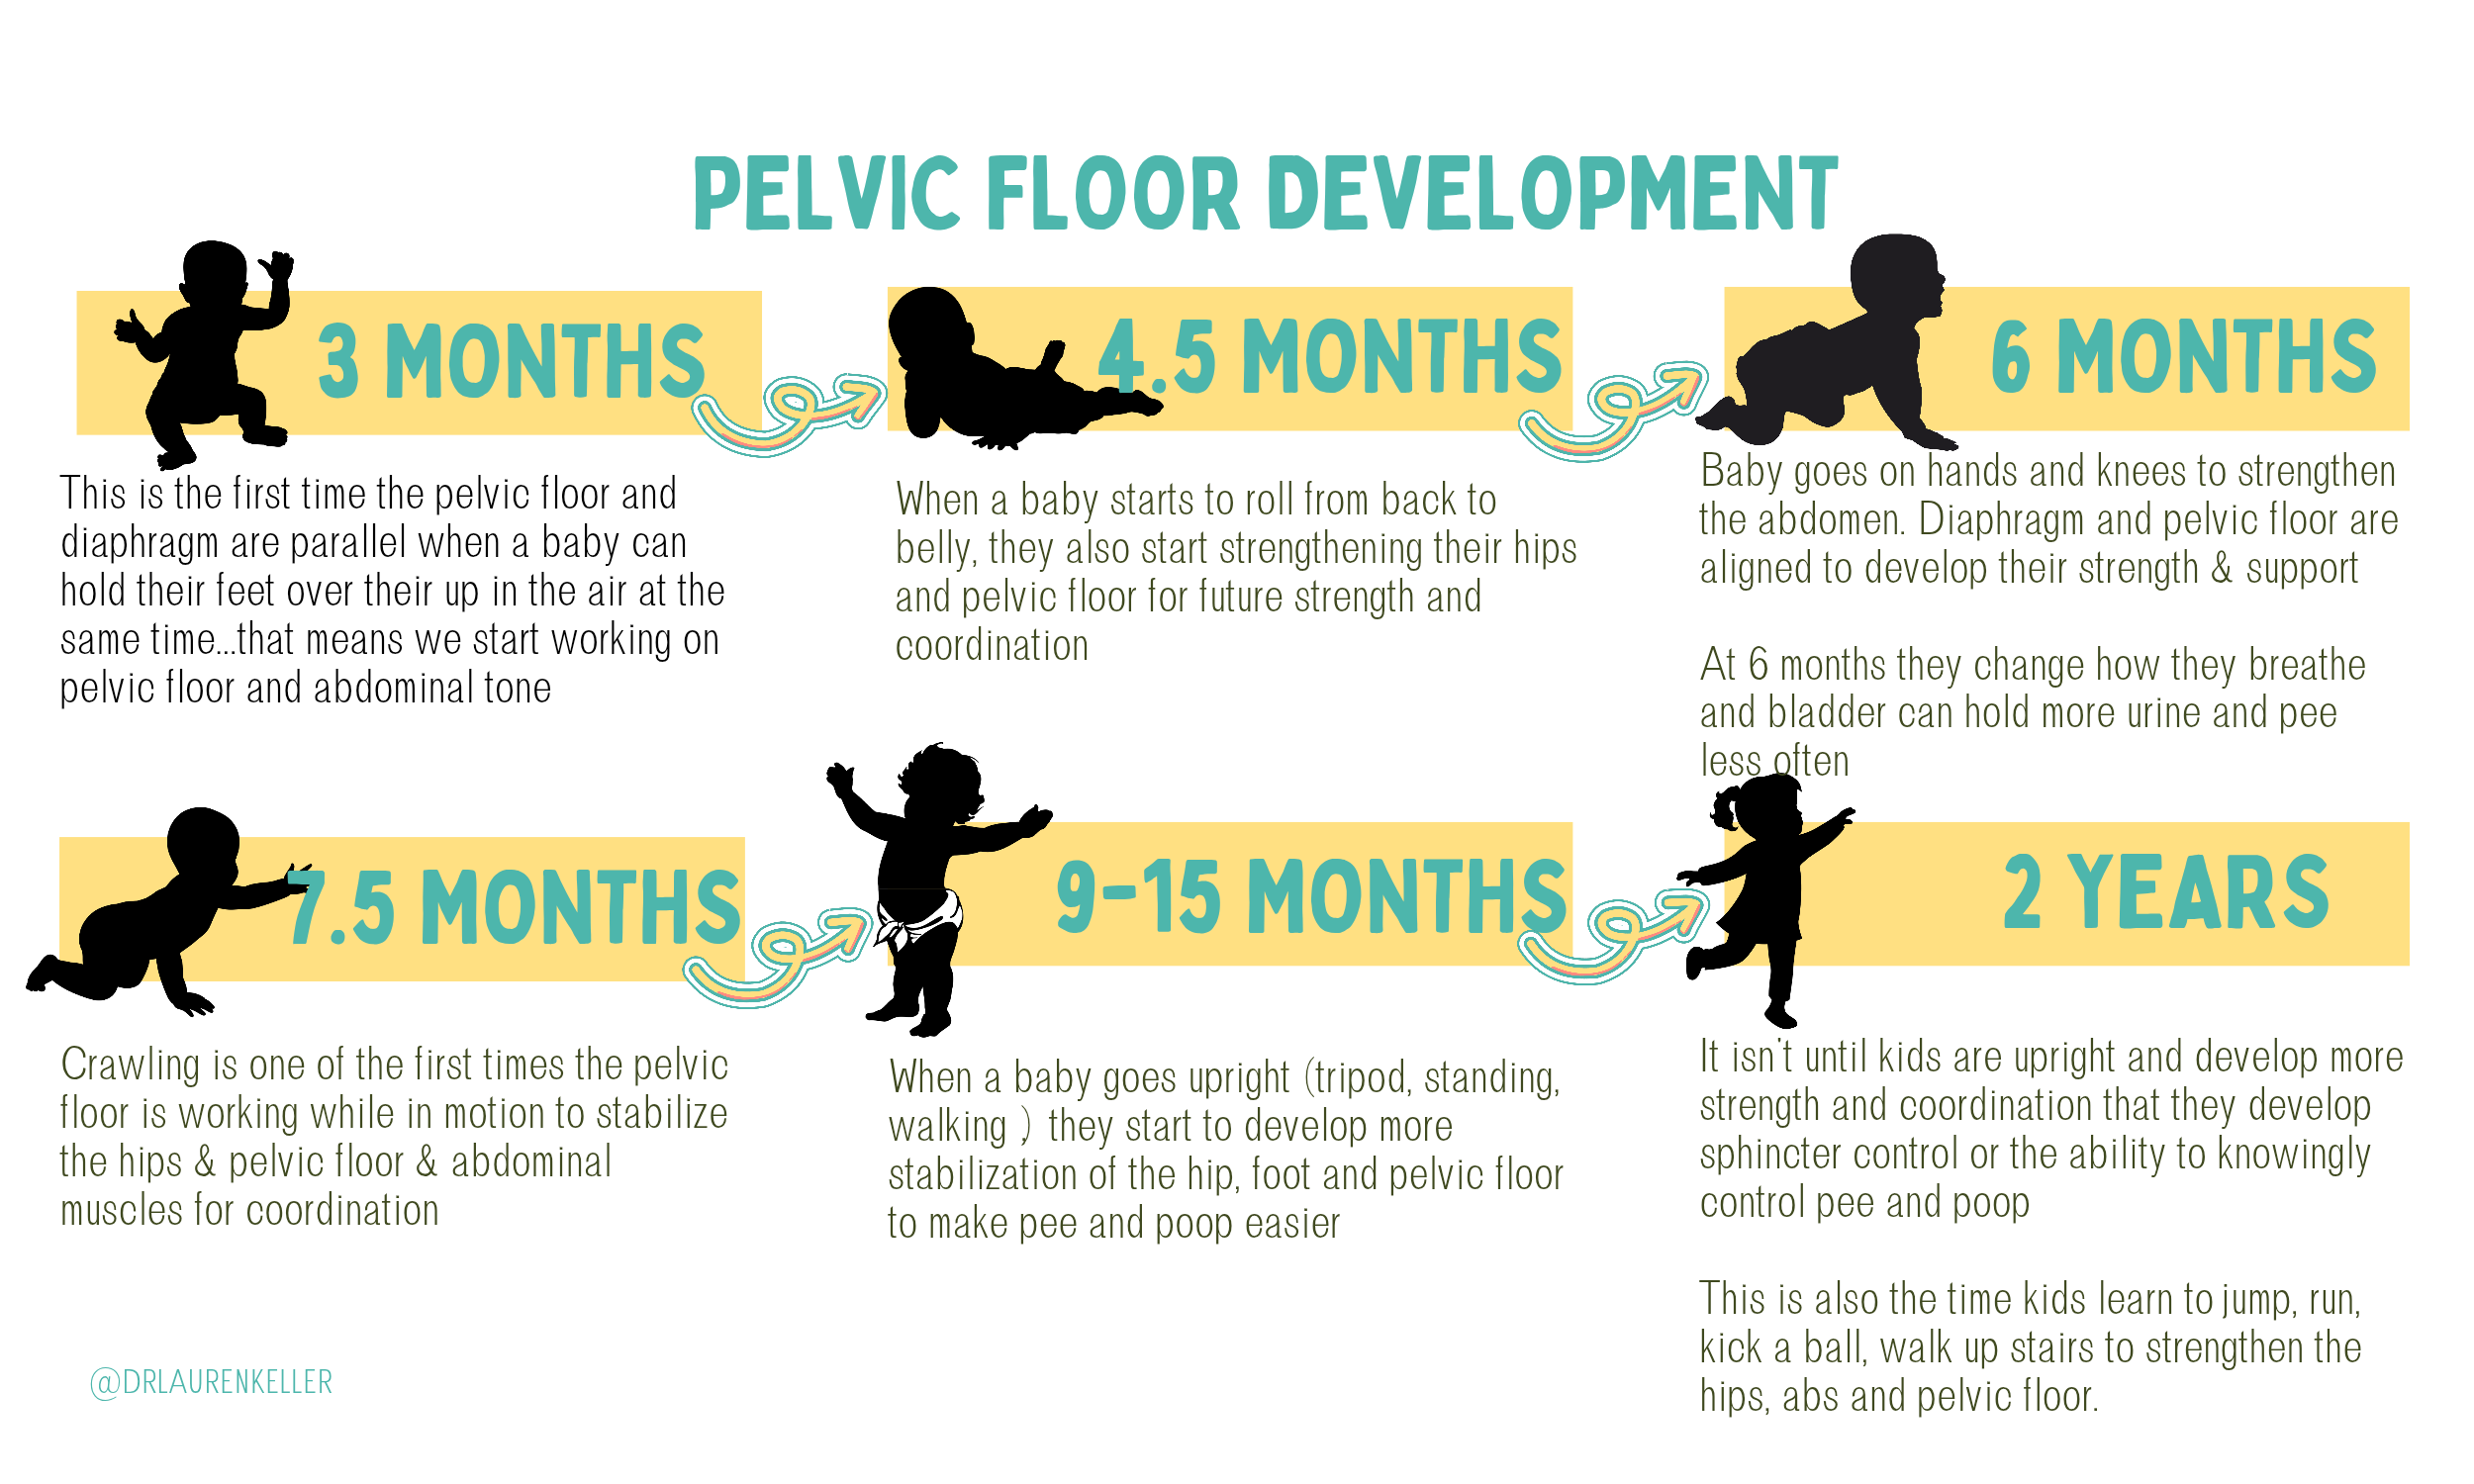
Next, let's think about how babies lie at rest…they generally have “baby bellies” where their stomachs stick out and they have a slight arch in the low back. As babies grow, their lower esophageal sphincter also grows and changes position. In babies the LES is located just above the diaphragm and by 6 months it moves to be level with the diaphragm. This arched newborn position makes it harder for the LES to function optimally. In infants younger than six months, they typically have a liquid-only diet (breastmilk, formula or combo feeding) and in addition to their weak lower esophageal sphincter, the sphincter sits at a slight angle along that normal baby belly arch. These babies also tend to be happy spitters and improve at 4 months and resolve completely at 6-7.5 months when babies start to go on all-fours and more upright, allowing the sphincter to move into a more neutral position and open/close freely.
Causes of Reflux that Need More Support
Dysbiosis and GI Inflammation
Dysbiosis is a fancy way to say that a child's gut microbiome is altered. This can be from genetics, maternal dysbiosis, premature birth and/or antibiotic use. Gut dysbiosis, food allergies, mold, and parasites can all lead to GI inflammation. This inflammation can cause increased pressure on the LES. The most common food allergy in infants is CMPA, or cow’'s milk protein allergy. For these babies, removing cow's milk and soy from both infant and mother's diet can decrease reflux. For other babies, a probiotic like l. reuteri can be helpful by decreasing dysbiosis and inflammation.
Visceral Hyperalgesia or Hypersensitivity (includes family history of Neurodivergence, ADHD or Autism)
Have you ever eaten something spoiled and had food poisoning? It starts as uncomfortable vomiting and by the end every ounce of your body is in pain. While this comes from dehydration, it’s also because your body has become hypersensitive to the pain…meaning it registers more pain than normal. Hypersensitivity can also increase in kids that don't sleep well. Either way, some babies feel every small change in body sensation.
The ability to feel pain, pressure and inflammatory changes is called interoception. In neurodivergent people (ADHD, ASD), interoception can be altered with both hyperawareness and decreased awareness. Just as adults feel increased pain with food poisoning, infants can have the same thing happen to them when they have reflux. Their brains experience more pain/awareness related to inflammation and distension in the esophagus and stomach. For these babies, it's important to focus on a whole body approach – decreasing inflammation, increasing comfort/vagal tone and supporting the body as a whole.
Low Vagal Tone or Vagal Reactivity
You've probably heard about “vagal exercises” for stress in adults. When we think of kids, we often hear “all they do is eat, sleep, pee and poop – what do they have to be stressed about?”. While I get the sentiment, it's important to remember that a lot more goes into infant stress response. When it comes to infants being stressed, it includes body stressors like birth trauma, maternal stress, premature birth, environmental concerns (toxins, allergens), missed naps, sleep disordered breathing and obstructive sleep apnea and even sensory differences.
It's also a fun fact that the vagus nerve plays an important role in digestion. The vagus nerve supplies part of the transverse colon, helping food move through the digestive tract. If a baby has slow digestion, the vagus nerve is frequently the cause. This is a two-way street, and gut inflammation can also increase stress on infants.
A few ways to support vagal tone includes massaging (or using a vibration tool) in front of the ear, skin-to-skin contact, singing, babywearing, infant massage and rhythmic movements.
Delayed Milestones, Arching of Back, Hernias, Rectus Abdominis
If we recap the growth and change of development from infancy to 6 months, it's important to highlight the LES moving position to be at the level of the diaphragm. The change in location allows the diaphragm to act as a sling to help support the LES. Any delay or modification in developmental milestones can change the LES. This can be any change from a newborn lifting their head or rolling before 3 months to a baby hating tummy time, a baby frequently arching their back or doing “baby sit-ups” to not being able to hold their feet over the ground when they are on their back.
If a baby is born with a hernia or noticeable rectus abdominis separation, this may delay the natural changes of pelvic floor and diaphragm development. If one parent is hypermobile, this can also delay milestones and increase reflux as the sphincters are hypermobile. Additionally, if a child is hypermobile they may have delayed milestones because their body needs increased support and stability.
Feeding Support / Tubes
NG-tubes and Orogastric tubes naturally keep the LES open. The breakdown of foods also begins in the mouth with enzymes breaking food down. By skipping this part of digestion, it can cause increased gas as the other parts of digestion have to work harder for normal digestion. For these babies, time is the best thing for your little one as the priority is making sure they are able to take in the nutrition needed.
Surgery
Surgery anywhere in the chest and abdomen can also alter reflux. Whether a child needed cardiopulmonary bypass, congenital heart defects, or abdominal surgery, all of these can alter the pressure in the abdomen and chest. If a baby had surgery and now has reflux, finding a provider who can do scar tissue massage can be helpful to help babies relieve reflux.
Constipation and GI Obstruction
This one is a two-way street, where constipation can increase reflux and reflux can increase constipation. Reflux causes babies to have increased pressure in the chest. Constipation causes babies to have increased pressure in the lower abdomen. The LES lies in between those areas and when either/both of those areas have higher pressure, the LES isn't able to fully close and stay closed. This constant fluctuation and battle between pressures can increase both constipation and reflux.
It's important to note that if a baby is projectile vomiting (3-4 feet) after eating, losing weight, dehydrated or not having regular bowel movements, the baby needs to be seen by the pediatrician as soon as possible.
Aerophagia: Breathing, Oxygen Support, Excessive Crying
Babies that need meconium aspiration or oxygen support are more likely to have reflux. Babies that breathe with their mouth open or take in extra air while eating are also more likely to have reflux. The area that we transport air (trachea and larynx) and the area we transport food (esophagus) sit right next to each other (and share a pathway in the nose and mouth area). Sometimes when we take in extra air or breathe with our mouth open the air goes into the stomach rather than the lungs. When this happens, reflux can happen because the pressure is too high because there is too much air in the stomach. This can also happen when a baby cries a lot or has frequent hiccups.
Aerophagia: Overfeeding, Shaking Formula Too Much, Wrong Bottle/Nipple, Unrealistic Expectations
Aerophagia was mentioned above, but it can increase anytime a baby takes in too much air. If a mother has an over-active letdown, babies may break the seal and take in more air. Happy spitters sometimes take in too much milk at the breast and then spit out what is extra. These babies are generally happy, the spit up looks like milky drool or a little extra spit up, and the milk doesn't smell sour/partially digested. Overfeeding can also occur with unrealistic expectations. This can be from parents misunderstanding baby's cues, unrealistic societal expectations around sleep, and giving too much formula/breastmilk. Most breastfed babies will eat 2-4oz from birth to one because the composition of breastmilk naturally changes to meet the baby's needs. Meanwhile, formula fed babies will increase their intake from 2-3oz at birth to 6-8oz by the age of one. This often leads to breastfed children being overfed because “they must be hungry” for only eating 3oz. On the other hand, formulas that are shaken too much, or using the wrong bottle or nipple for the baby's mouth can lead to increasing air in the stomach.
Tongue tie, Cleft Palate, Cleft Lip, Oral Motor Dysfunction (Suck-Swallow-Breathe Coordination Issue),
Tongue tied babies may develop increased reflux at 3-4 months of age when more controlled oral-motor coordination is needed for nursing. If a baby has a tongue tie, you may notice that they frequently have their mouth open, or that the corners of their mouth aren't able to fully close on the nipple/bottle. This can prevent the tongue from creating a good seal on the roof of the mouth and allow extra air into the stomach. These babies also frequently have a suck-swallow-breathe pattern that isn't maturing as we expect. In these cases, working with someone trained in infant oral motor work (SLP, OT, PT, DC) will be the best solution to making sure your baby has appropriate oral motor coordination and strength and can help guide you in knowing when your baby is ready for a tongue tie release and do post-operative exercises to help your child continue developing strength.
Reflux treatment is so much more than acid blocking medications. In order to fully help your child, it's important to look at all aspects of their body, birth, development and emotional regulation. My hope is that this blog either helps guide you to the right provider(s) for your child or gives you the confidence you need to know that time will help.